

Cardiology Audit Checklist: Complete Billing, Coding and Compliance Guide

Cardiology billing involves specialized diagnostic tests, invasive procedures, imaging studies, and ongoing patient management. Each service must be supported by clinical documentation, accurately coded, and billed according to applicable insurance requirements. A single coding or documentation error can result in a denied claim, incorrect reimbursement, or an audit finding.
A cardiology audit checklist helps healthcare providers, medical billers, and coders examine these risks before they affect reimbursement or create compliance problems.
According to the Centers for Medicare & Medicaid Services (CMS), the estimated Medicare fee-for-service improper payment rate for fiscal year 2025 was 6.55%, representing approximately $28.83 billion. This figure covers Medicare fee-for-service claims across multiple healthcare settings, rather than cardiology alone.
Regular claim reviews help cardiology practices identify unsupported charges, verify medical necessity, detect coding mistakes, and correct weaknesses in their billing procedures.
What is a cardiology billing audit?
A cardiology billing audit is a structured examination of medical records, procedure codes, insurance claims, payment information, and compliance requirements associated with cardiovascular services.
Auditors compare documented clinical services against submitted claims to determine whether each charge is accurate, medically justified, and consistent with payer policies.
The review commonly includes office consultations, echocardiography, electrocardiograms, cardiac stress testing, ambulatory rhythm monitoring, cardiac catheterization, coronary interventions, and cardiac rehabilitation.
Two types of reviews are particularly useful.
Prospective audits examine claims before submission. These reviews can identify missing documentation, coding errors, and incorrect modifiers while corrections are still possible.
Retrospective audits evaluate claims that have already been submitted or paid. They help identify recurring errors, potential overpayments, and problems that require corrective action.
Both approaches should evaluate undercoding as well as overcoding. An audit limited to denied claims may overlook services that were billed incorrectly but still received payment.
Cardiology audit checklist for accurate billing and compliance
The following checklist covers the principal areas that cardiology practices should examine during internal billing audits.
1. Verify patient and insurance information
Before reviewing procedure codes, confirm that the claim contains accurate patient identifiers, insurance coverage information, and provider details.
Check whether coverage was active on the date of service and whether the claim was directed to the appropriate payer.
Review the following information:
- Patient name, date of birth, and insurance identification number
- Insurance eligibility and applicable benefits
- Primary and secondary payer information
- Rendering provider NPI and billing provider information
- Service location and date of service
- Referral or prior authorization requirements
For Medicare beneficiaries, auditors should also verify whether the patient was enrolled in Original Medicare or a Medicare Advantage plan. These arrangements may have different authorization, network, and claim submission requirements.
2. Confirm medical necessity for cardiovascular services
Medical necessity is one of the most important elements of cardiology compliance.
A documented diagnosis alone does not automatically establish that a diagnostic test or procedure was necessary. The medical record should explain the patient's condition, relevant symptoms, clinical findings, and reason for the ordered service.
For example, a patient undergoing stress echocardiography should have documentation explaining why the study was selected.
CMS Medicare billing and coding article A57183, revised effective October 1, 2026, addresses documentation requirements for cardiovascular stress testing. It identifies clinical diagnosis, the reason for testing, the choice of stress echocardiography, and the justification for pharmacological stress when applicable.
Auditors should also examine repeated diagnostic testing. An additional study may require documentation showing a change in symptoms, clinical status, or another medical reason for reassessment.
3. Review cardiology CPT coding accuracy
Cardiology procedures often involve multiple components, making CPT code selection particularly sensitive to documentation details.
Auditors should determine whether the submitted code accurately describes the service performed.
Common codes requiring careful review include:
| CPT code | Cardiology service |
|---|---|
| 93000 | Routine 12-lead ECG with tracing, interpretation, and report |
| 93005 | ECG tracing only |
| 93010 | ECG interpretation and report only |
| 93306 | Complete transthoracic echocardiography with spectral and color Doppler |
| 93308 | Limited or follow-up transthoracic echocardiography |
| 93015 | Global cardiovascular stress testing service |
These examples do not replace current CPT instructions or payer-specific policies.
A coder should never select a more extensive procedure code simply because additional services are typically performed in the department. The documentation must support the actual service represented by the code.
4. Audit evaluation and management services
Office and outpatient evaluation and management (E/M) services require appropriate documentation of medical decision-making or qualifying total time, depending on the method used to select the code.
For cardiology encounters, auditors should review the problems addressed, diagnostic information considered, treatment decisions, and patient management risks.
A routine follow-up involving stable disease may support a different E/M level from an encounter involving worsening symptoms, medication adjustments, and a decision about additional testing.
Special attention is necessary when an E/M service is billed on the same day as a cardiac procedure.
Modifier 25 may be appropriate when a significant, separately identifiable E/M service is documented. The routine assessment associated with performing a cardiac stress test does not independently justify a separate E/M charge.
CMS addresses this distinction in its 2026 National Correct Coding Initiative (NCCI) Policy Manual.
5. Check diagnostic testing components and modifiers
Cardiology practices frequently perform tests that include technical and professional components.
The technical component generally covers equipment, supplies, technical personnel, and test acquisition. The professional component involves physician interpretation and reporting.
For eligible diagnostic codes, modifier 26 identifies the professional component, while modifier TC identifies the technical component.
However, these modifiers cannot automatically be applied to every diagnostic procedure.
For example, CPT 93005 already represents the technical portion of a routine ECG, while CPT 93010 represents the interpretation and report. These standalone codes should not receive modifiers 26 or TC.
Auditors should verify that the practice billed only the components it actually provided and that separate billing entities did not duplicate the same service.
6. Examine echocardiography documentation
Echocardiography claims deserve specific attention because complete and limited studies have different coding requirements.
CPT 93306 describes a complete transthoracic echocardiographic examination that includes the applicable spectral and color Doppler components.
CPT 93308 applies to limited or follow-up transthoracic studies.
A limited examination should not be billed as a complete study when the required examination components were not performed and documented.
For example, a follow-up echocardiogram performed specifically to assess an existing pericardial effusion may support limited-study coding when the examination's scope matches the documentation.
Auditors should examine image acquisition records, the signed interpretation, the clinical indication, and any separately reported Doppler services.
7. Review cardiac stress testing claims
Cardiac stress testing may involve exercise or pharmacological stress, ECG monitoring, imaging, supervision, interpretation, and reporting.
The audit should determine which components were actually furnished and which are included in the reported service.
CMS's 2026 NCCI guidance explains that routine ECG recordings and certain access or administration services are included in cardiovascular stress testing and should not be separately billed merely because they occurred during the test.
For pharmacological testing, verify the reason for using medication rather than exercise.
The report should support the service performed, and any separate medication billing must satisfy applicable code and payer requirements.
8. Audit cardiac catheterization and coronary interventions
Invasive cardiology claims require detailed comparison between procedure reports and submitted codes.
Review the catheterization findings, coronary anatomy, vessels treated, interventions performed, and documented medical necessity.
For percutaneous coronary interventions, coding depends on the specific treatment, coronary vessel, branch, and applicable CPT instructions.
Routine vascular access, ECG monitoring, and fluoroscopic guidance may be included in the primary procedure rather than separately reportable.
An auditor should also check whether a diagnostic catheterization performed with an intervention meets the requirements for separate reporting.
The operative report should be the primary source for these decisions, supplemented by relevant images and clinical documentation when necessary.
9. Verify cardiac rehabilitation services
Cardiac rehabilitation claims require documentation of patient eligibility, services provided, session duration, and applicable supervision.
Medicare generally allows an initial course of 36 regular cardiac rehabilitation sessions over a maximum of 36 weeks, subject to program rules and provisions for additional sessions.
Auditors should compare attendance records, treatment documentation, and billed units.
CMS's 2026 Physician Fee Schedule policies also permit real-time audio-video direct supervision for certain eligible services, including cardiac rehabilitation, subject to applicable requirements. Audio-only communication does not satisfy this virtual direct-supervision provision.
10. Check coding edits and modifier use
CMS maintains NCCI procedure-to-procedure edits to prevent inappropriate billing of services that should not be reported together.
The audit should examine:
- Unbundled services
- Duplicate procedure charges
- Incorrect modifier 25 use
- Unsupported modifier 59 or X modifiers
- Incorrect units of service
- Medically unlikely edits (MUEs)
- Missing or incorrect add-on codes
NCCI edits are updated at least quarterly, so auditors must use the version applicable to the date of service.
A modifier should be assigned because documentation supports a legitimate coding exception, rather than simply to bypass a claim rejection.
11. Review authorizations, claim submission, and reimbursement
The final claims review should connect the clinical record with the financial outcome.
Auditors should verify required authorizations, correct place-of-service coding, timely submission, contractual payment terms, and accurate payment posting.
Compare the payer's allowed amount with the applicable contract and review contractual adjustments, patient responsibility, and any remaining accounts receivable.
A paid claim is not necessarily compliant. Payers may reimburse claims that contain coding errors, making retrospective reviews necessary even when denial rates appear low.
How to conduct an internal cardiology billing audit
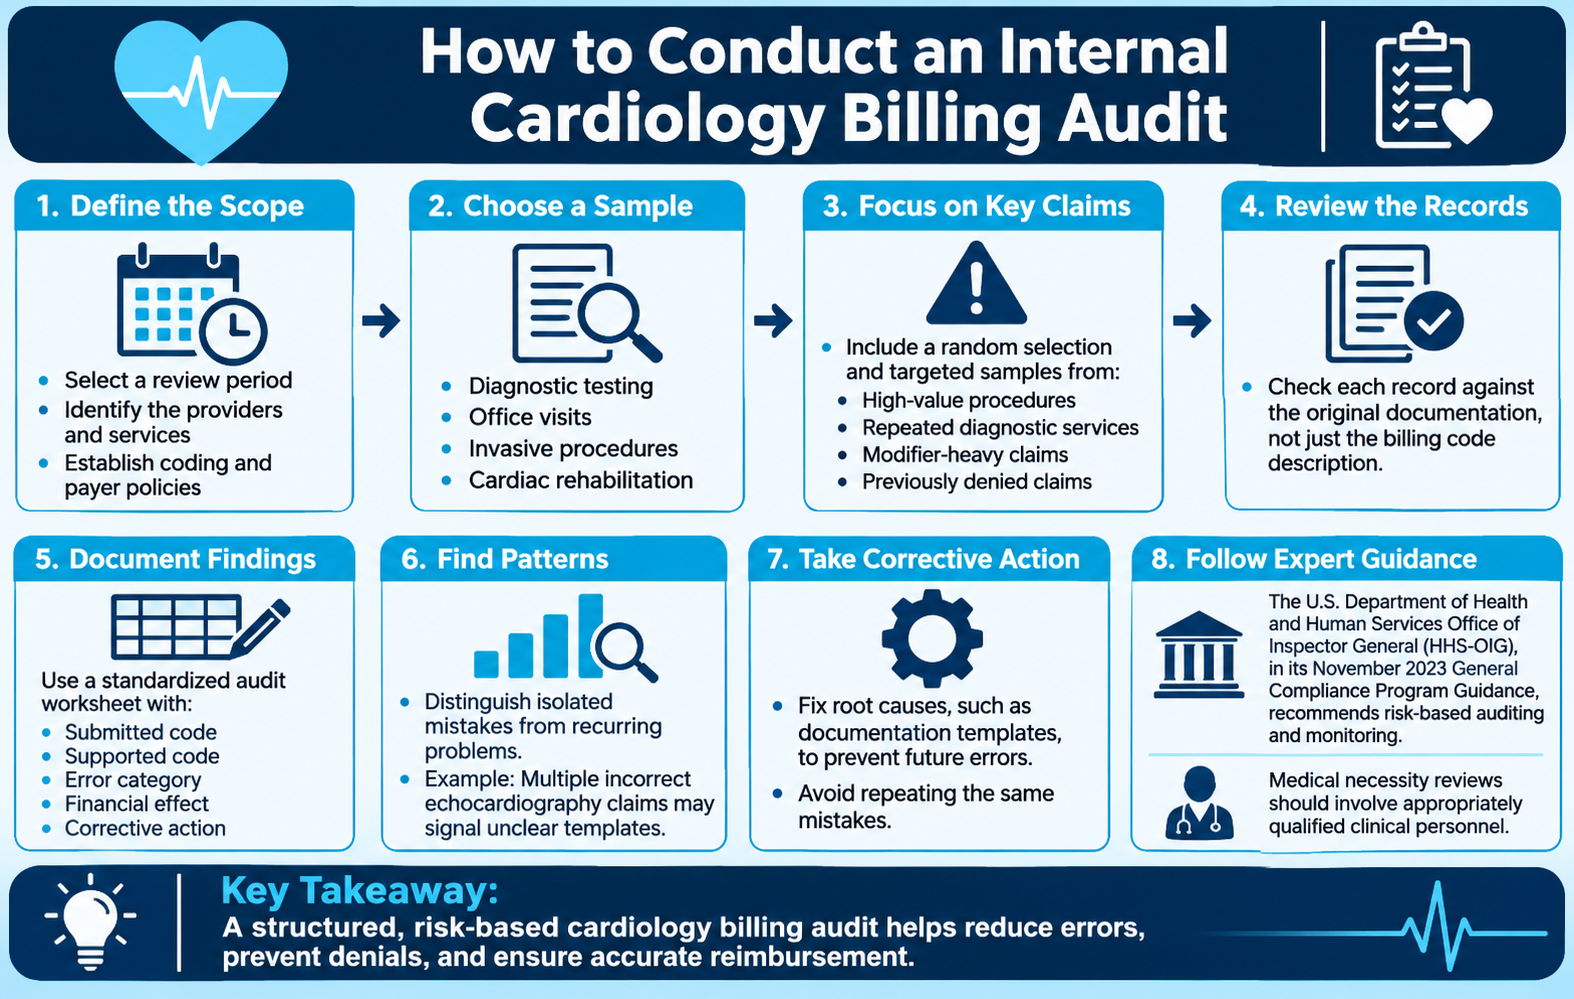
An effective audit begins with a defined scope.
Select a review period, identify the providers and services involved, and establish the coding and payer policies applicable to those claims.
A practical approach is to divide the sample into diagnostic testing, office visits, invasive procedures, and cardiac rehabilitation.
Include a random selection of claims alongside targeted samples from higher-risk categories, such as high-value procedures, repeated diagnostic services, modifier-heavy claims, and previously denied claims.
Each record should be examined against the original documentation rather than the billing system's code description alone.
Record findings in a standardized audit worksheet containing the submitted code, supported code, error category, financial effect, and corrective action.
Once the review is complete, distinguish isolated mistakes from recurring problems.
For example, multiple incorrect echocardiography claims may indicate that the department's documentation templates do not clearly identify whether studies are complete or limited.
Correcting that template may prevent future errors more effectively than repeatedly changing individual claims.
The U.S. Department of Health and Human Services Office of Inspector General (HHS-OIG), in its November 2023 General Compliance Program Guidance, recommends risk-based auditing and monitoring as elements of an effective compliance program.
Medical necessity reviews should involve appropriately qualified clinical personnel rather than relying entirely on administrative coding checks.
Common cardiology billing audit findings
Several problems recur across cardiovascular billing workflows.
Insufficient documentation: The claim identifies a service, but the medical record does not fully establish the clinical reason, procedure scope, or completed interpretation.
Incorrect diagnostic components: A practice bills a global diagnostic service despite performing only the technical or professional portion.
Unbundled charges: Services already included in a cardiovascular procedure are separately reported without a valid exception.
Unsupported E/M levels: The selected visit level exceeds what the documented medical decision-making or qualifying time supports.
Authorization problems: A service requires payer approval, but the approval is missing, expired, or inconsistent with the service billed.
For every finding, the audit should identify the responsible workflow and required correction. Potential overpayments must be evaluated under applicable refund and reporting requirements.
How often should cardiology practices perform audits?
There is no universal audit interval that fits every cardiology practice.
Frequency should reflect claim volume, service complexity, previous audit findings, payer changes, and the organization's compliance risk assessment.
Monthly targeted reviews can help monitor recently identified problems, while broader periodic audits can evaluate performance across providers and service categories.
New cardiologists, newly introduced procedures, revised coding rules, and repeated payer denials may justify additional reviews.
The practice should also verify that corrective actions remain effective by reexamining relevant claims after staff training or workflow changes.
Strengthening cardiology billing compliance
A ardiology audit checklistgives practices a consistent method for testing billing accuracy against clinical documentation and payer requirements.
The most useful audits examine the full claim history, from medical necessity and procedure documentation to coding, submission, payment, and correction of identified errors.
CMS's 2026 coding policies and HHS-OIG compliance guidance provide a foundation for these reviews, but practices must also check applicable Medicare Administrative Contractor instructions and individual payer policies.
Regular documentation reviews, clinician involvement, and follow-up testing of corrections help identify billing errors before they become repeated compliance problems.



