Stress Test Billing Guide: CPT Codes, Modifiers, Documentation & Reimbursement

Cardiac stress testing helps physicians evaluate how the heart responds to physical exertion or medication-induced stress. For medical billing teams, these procedures require careful code selection because the claim may involve test supervision, ECG tracing, interpretation, cardiac imaging, and pharmacological agents.
A reliable stress test billing guide should begin with the service actually performed. CPT codes 93015, 93016, 93017, and 93018 divide cardiovascular stress testing into different billing components. Selecting the wrong code can result in duplicate charges, incorrect reimbursement, or claim denials.
This guide explains the principal stress test CPT codes, common modifiers, documentation requirements, and payment considerations for cardiology practices and medical billing professionals.
Understanding cardiovascular stress test CPT codes
The primary CPT code family for conventional cardiovascular stress testing is 93015–93018. These codes distinguish between complete service billing and individual components.
CPT 93015
CPT 93015 represents the complete cardiovascular stress test, including physician supervision, ECG monitoring, interpretation, and report. It applies when the billing provider is responsible for the entire service.
CPT 93016
CPT 93016 represents physician supervision without interpretation and reporting. It may apply when a physician supervises the test while another qualified professional performs the interpretation.
CPT 93017
CPT 93017 represents the technical tracing component without supervision or interpretation and reporting. It generally applies when a facility or qualified supplier provides the technical portion of the procedure.
CPT 93018
CPT 93018 represents interpretation and reporting without the other stress-testing components. The interpreting provider must review the recorded findings and prepare a report documenting the results.
The four codes should not automatically appear together on every claim. Billing depends on which provider or facility performed each component and the applicable professional or facility payment rules.
Stress echocardiography CPT codes
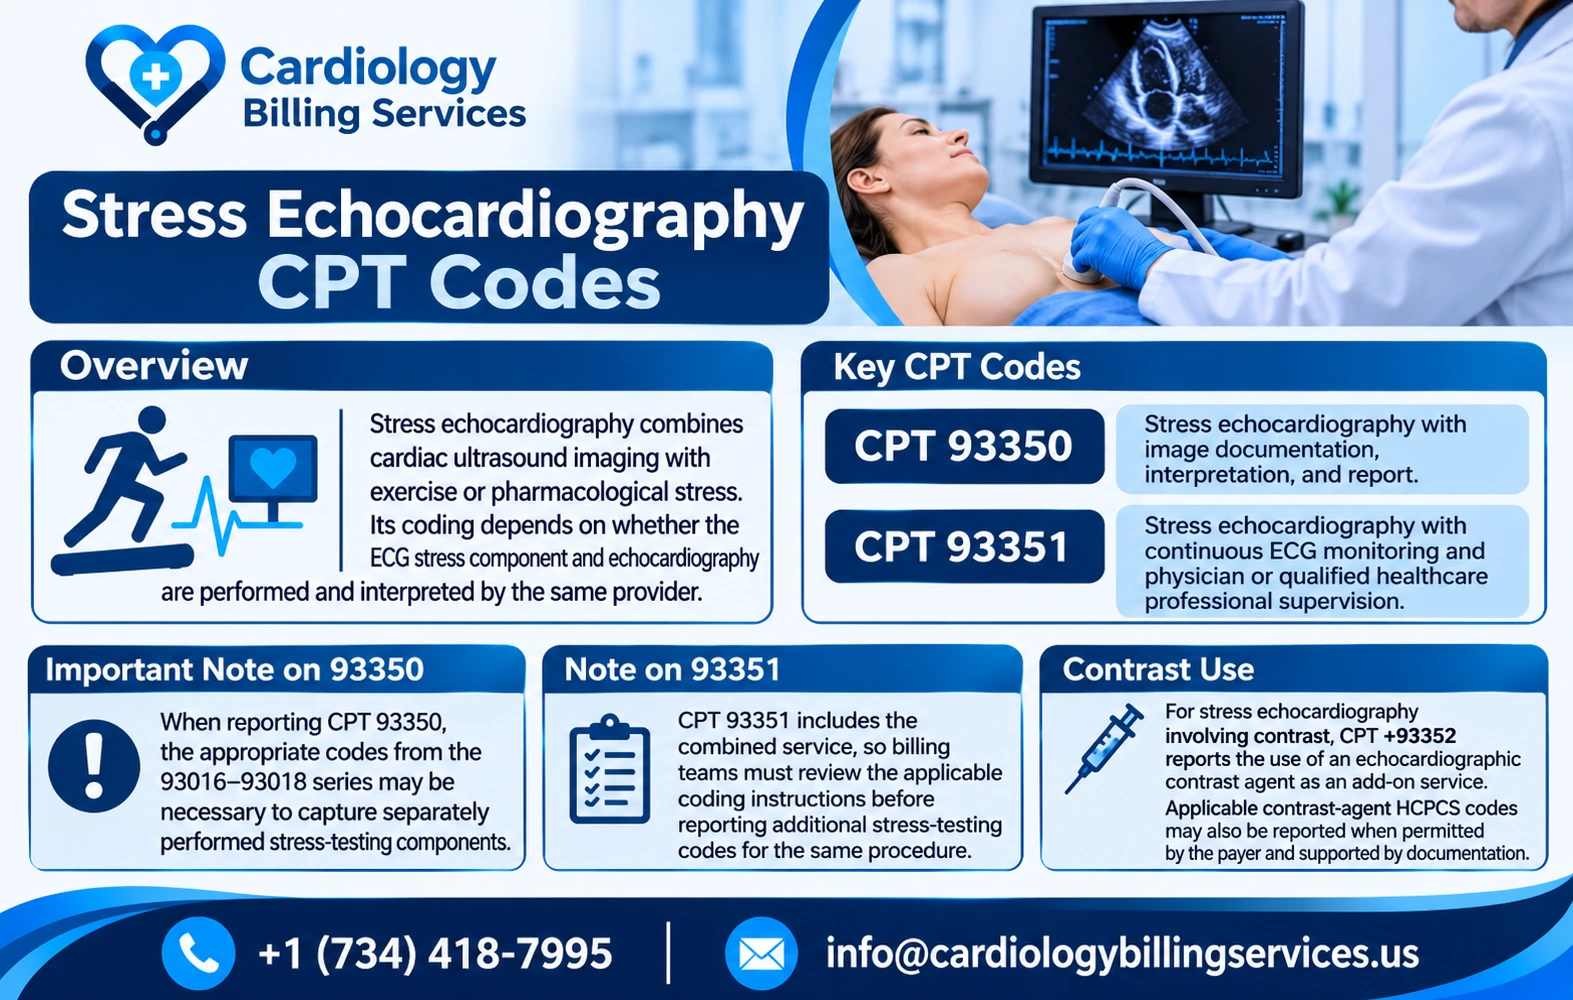
Stress echocardiography combines cardiac ultrasound imaging with exercise or pharmacological stress. Its coding depends on whether the ECG stress component and echocardiography are performed and interpreted by the same provider.
CPT 93350
Two codes are particularly important. CPT 93350 represents stress echocardiography with image documentation, interpretation, and report.
CPT 93351
CPT 93351 describes stress echocardiography that also includes continuous ECG monitoring and physician or qualified healthcare professional supervision.
When reporting CPT 93350, the appropriate codes from the 93016–93018 series may be necessary to capture separately performed stress-testing components. CPT 93351 includes the combined service, so billing teams must review the applicable coding instructions before reporting additional stress-testing codes for the same procedure.
CPT +93352
For stress echocardiography involving contrast, CPT +93352 reports the use of an echocardiographic contrast agent as an add-on service. Applicable contrast-agent HCPCS codes may also be reported when permitted by the payer and supported by documentation.
Common modifiers used in stress test billing
Modifier selection depends on the procedure code, service location, and provider responsibilities. Applying modifiers without checking the code’s billing instructions can create reimbursement problems.
Modifier 26 (Professional Component)
Modifier 26 (Professional Component) identifies the professional portion of an eligible diagnostic service when the physician provides interpretation and reporting while another entity supplies the technical resources. For example, CPT 93351-26 may be appropriate when the physician provides the professional component of a stress echocardiogram in a facility setting, subject to the applicable code and payer instructions.
Modifier TC (Technical Component)
Modifier TC (Technical Component) identifies the technical portion of an eligible diagnostic service when the facility or supplier provides the equipment, supplies, and technical resources. Billing teams should verify the code’s professional and technical component indicators before reporting this modifier.
Modifier 59 (Distinct Procedural Service)
Modifier 59 (Distinct Procedural Service) may be appropriate when two otherwise restricted services are genuinely separate and documentation supports the distinction. It should never be added simply to bypass a National Correct Coding Initiative edit or obtain separate payment for an included service.
One important distinction is that CPT 93015 represents the complete stress-testing service. The professional and technical components should not be separated by appending modifiers 26 or TC to this complete-service code. When different entities perform individual components, the appropriate codes from 93016 through 93018 should be considered.
Documentation requirements for stress test claims
Medical necessity and a complete procedure report determine whether a stress test claim can withstand payer review. The medical record should explain why the physician ordered the test and establish which services were performed.
The documentation should identify the patient’s clinical diagnosis, the reason for ordering the procedure, and the referring physician’s order. When stress echocardiography is performed, the record should explain the clinical reason for selecting imaging rather than an ECG-only stress test when that distinction is relevant to coverage requirements.
The report should also document the stress method, exercise duration or medication administered, relevant heart rate and blood pressure findings, ECG changes, patient symptoms, and the reason for terminating the test. Interpretation and reporting should reflect the actual findings. For stress echocardiography, the report should address the relevant resting and stress imaging results.
When pharmacological stress is used, the documentation should explain why the patient could not adequately exercise or why medication-induced stress was clinically appropriate. The medication administered, dosage, and other relevant administration details should be recorded.
Medicare documentation requirements also address repeat testing. Routine annual testing without individualized clinical indications is not automatically considered reasonable and necessary. The medical record must explain why another study is appropriate for the patient’s condition and current symptoms.
Medicare reimbursement for cardiovascular stress testing
Stress test reimbursement depends on the CPT code, place of service, provider participation, and payer reimbursement methodology.
Under the 2026 Medicare Physician Fee Schedule, payment calculations use three relative value unit components. The work RVU represents the physician’s time, effort, and clinical responsibility. The practice expense RVU accounts for expenses such as equipment, supplies, and clinical staff. The malpractice RVU reflects professional liability costs.
CMS applies geographic practice cost indices to adjust these components according to the Medicare payment locality. As a result, the allowed amount for the same procedure may differ between geographic areas.
The payment arrangement also differs between office-based and hospital-based services. A physician’s professional payment in a hospital setting generally reflects the professional work rather than the facility’s full technical expenses. Hospital outpatient reimbursement is calculated separately under applicable facility payment rules.
Billing teams should verify the applicable Medicare fee schedule amount using the patient’s date of service, geographic locality, and correct procedure code. Commercial insurers and Medicaid programs may use different fee schedules, contractual rates, and payment policies. The amount submitted on a claim should never be treated as the expected reimbursement.
Common stress test billing mistakes
Even when the correct procedure is performed, coding and documentation problems can delay payment. One frequent mistake is reporting CPT 93015 when the provider performed only one component of the procedure. Another is reporting CPT 93351 alongside separately included stress-testing services without checking the applicable coding rules.
Incorrect use of modifiers 26, TC, and 59 can also result in claim rejections or payment reductions. A modifier should reflect the actual service performed and the billing arrangement between the physician and facility.
Diagnosis selection requires equal attention. The diagnosis must reflect the patient’s documented condition and support the medical necessity of the ordered test. Billing teams should review the applicable Medicare Administrative Contractor coverage policy and the individual payer’s diagnosis requirements before submitting the claim.
A practical pre-submission review should compare the procedure report, provider responsibilities, CPT code, diagnosis, modifier, and place of service. This process helps identify coding inconsistencies before claims reach the clearinghouse.
Accurate stress test coding supports appropriate reimbursement
Successful stress test billing requires accurate CPT selection, appropriate component reporting, and documentation that supports medical necessity. Codes 93015–93018 distinguish the responsibilities involved in conventional cardiovascular stress testing, while 93350 and 93351 address stress echocardiography.
For cardiology practices, regular review of modifiers, Medicare coverage requirements, procedure reports, and locality-specific payment rates helps reduce avoidable denials. Medical billers and coders should also verify current-year CPT guidelines and individual payer policies before submitting claims, particularly when multiple providers participate in the same study.