

Cardiology A/R over 90 days: how to recover aging insurance payments

A cardiology claim that sits unpaid past 90 days has usually stopped being a payer delay and become a problem nobody owns. The visit note is filed, the echo report is signed, and the explanation of benefits (EOB) came back weeks ago with a code that no one acted on. Cardiology A/R over 90 days is where those orphaned claims collect, and recovering them takes a different method than routine follow-up.
This guide is written for practice owners, billing managers, and students training as billers and coders. It covers how to measure aging balances, why cardiology produces them so reliably, which deadlines still allow recovery, and how to work the backlog in a sensible order.
What counts as aging A/R in a cardiology practice
Accounts receivable reports sort unpaid balances into five buckets: 0 to 30, 31 to 60, 61 to 90, 91 to 120, and 121 days or more. The Medical Group Management Association (MGMA) uses these same bands in its benchmarking dashboards, and the last two make up the “over 90” figure.
The calculation is simple. Divide the dollar value of all balances older than 90 days by total A/R, then multiply by 100. A practice with $500,000 in total A/R and $90,000 older than 90 days sits at 18 percent. That is an arithmetic example, not a reported case.
What counts as healthy depends on whom you ask. The figure most often attributed to MGMA is 12 to 15 percent for high-performing groups, a range repeated in ModMed’s RCM benchmarking series. A 2023 KevinMD article on practice billing metrics recommends staying under 20 percent. Some billing firms push the target down to 10 percent. Pick one and keep it fixed so trend lines mean something.
One detail from that KevinMD piece deserves attention: measure age from the date of service, not the date a claim was rebilled. Resubmitting a denied claim resets the billing date in many systems and makes old problems look new. A report built on rebill dates will understate the true over-90 figure.
Days in A/R is the companion number. MGMA’s commonly cited target for physician groups is under 40 days. A practice can post 38 days and still carry a swollen tail, because the average hides it.
Why cardiology claims age faster than most specialties
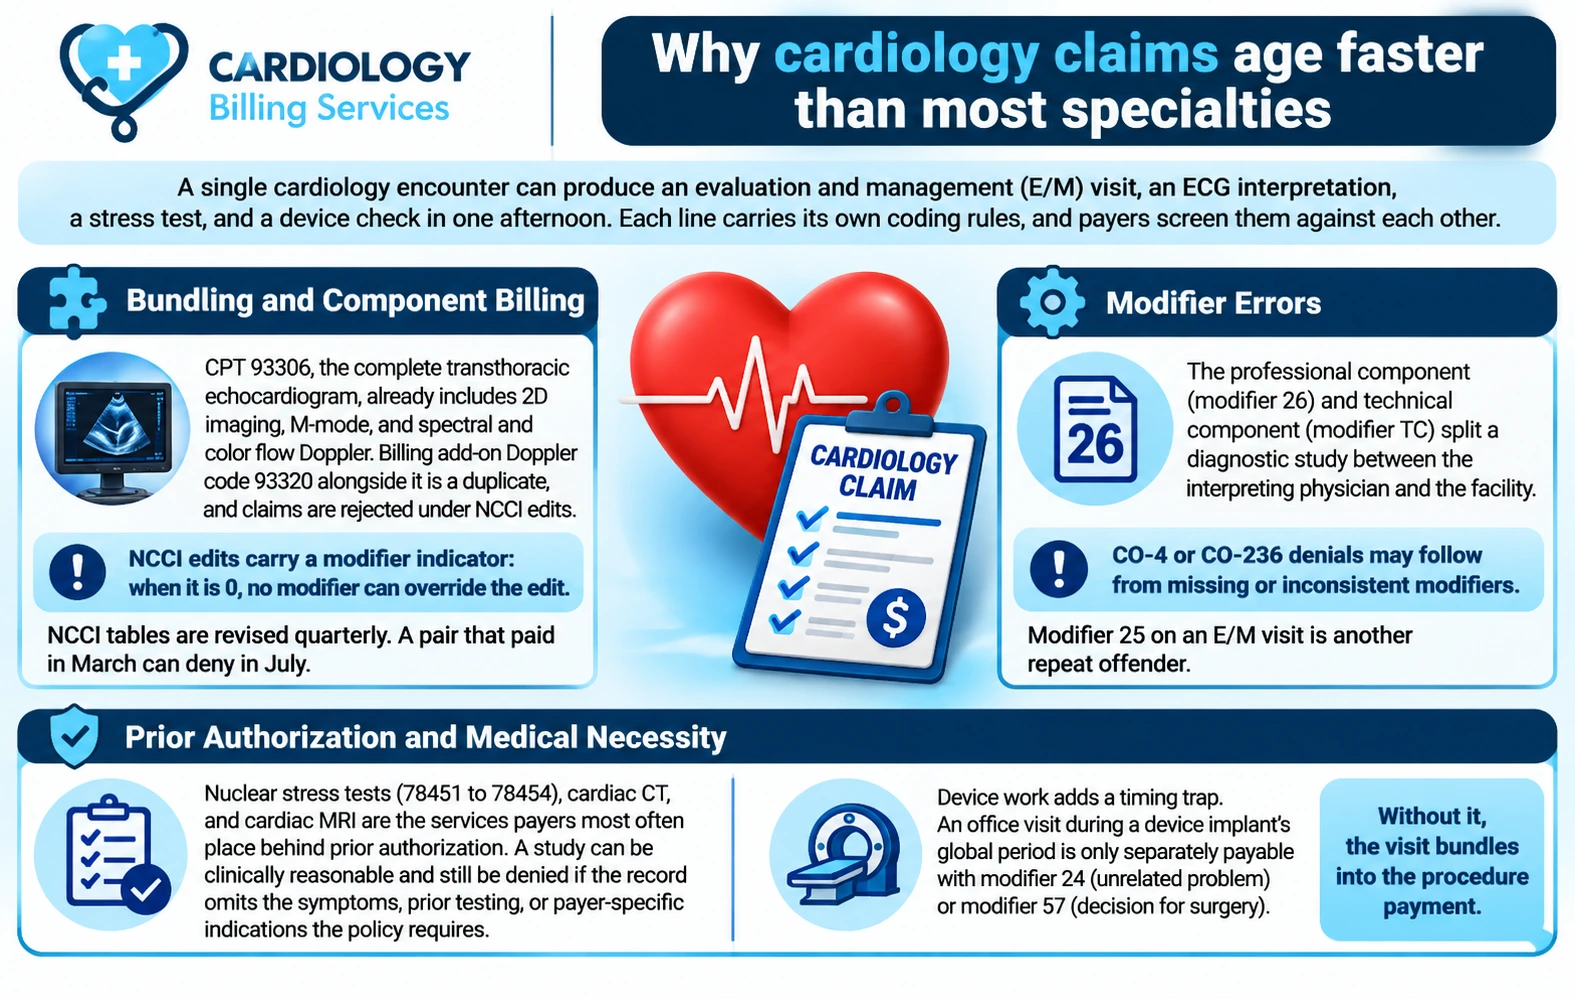
A single cardiology encounter can produce an evaluation and management (E/M) visit, an ECG interpretation, a stress test, and a device check in one afternoon. Each line carries its own coding rules, and payers screen them against each other.
Bundling and component billing
CPT 93306, the complete transthoracic echocardiogram, already includes 2D imaging, M-mode, and spectral and color flow Doppler. Billing add-on Doppler code 93320 alongside it is a duplicate, and claims are rejected under National Correct Coding Initiative (NCCI) edits. NCCI edits carry a modifier indicator: when it is 0, no modifier can override the edit, so resubmitting with modifier 59 only produces a second denial.
NCCI tables are revised quarterly. A pair that paid in March can deny in July without any change in your workflow.
Modifier errors
The professional component (modifier 26) and technical component (modifier TC) split a diagnostic study between the interpreting physician and the facility or equipment owner. Billing a global code from a hospital setting, where the hospital owns the equipment, produces CO-4 or CO-236 denials. CO-4 flags a missing or inconsistent modifier. CO-236 flags a procedure and modifier combination that is not compatible with another service billed the same day.
Modifier 25 on an E/M visit billed alongside a stress test or ECG is another repeat offender. Payers want documentation showing the visit addressed a problem separate from the test, and a note that simply lists the test result rarely meets that bar.
Prior authorization and medical necessity
Nuclear stress tests (78451 to 78454), cardiac CT, and cardiac MRI are the services payers most often place behind prior authorization. A study can be clinically reasonable and still be denied if the record omits the symptoms, prior testing, or payer-specific indications the policy requires. A nuclear stress claim with no supporting diagnosis, such as coronary artery disease or chest pain, will typically fail medical necessity review.
Device work adds a timing trap. An office visit during a device implant’s global period is only separately payable with modifier 24 (unrelated problem) or modifier 57 (decision for surgery) where applicable. Without it, the visit bundles into the procedure payment.
Deadlines that decide what can still be recovered
Before touching a single claim, check the clock. Under Original Medicare, a claim must reach the contractor within one calendar year of the date of service. Palmetto GBA, a Medicare Administrative Contractor (MAC), states that claims denied for timely filing are not eligible for redetermination because no initial determination was made.
For claims that were processed and denied, the first appeal level is redetermination, and the request must be filed within 120 days of receiving the initial determination notice (the remittance advice or Medicare Summary Notice). Palmetto GBA allows a five-day mailing grace period and may extend the window for good cause. The second level, reconsideration by a Qualified Independent Contractor, must be requested within 180 days of the redetermination notice.
Palmetto’s own example makes the stakes plain. A remittance dated May 15, 2020, checked on October 15, was 153 days old, and appeal rights had ended on September 17. That cardiology claim sitting in your 120-plus bucket may already be past saving through appeal, so the age of the denial notice, not the age of the service, sets the priority.
Commercial and Medicaid rules differ. Medicaid filing and appeal windows are set by each state, and commercial deadlines come from the provider contract. Build a payer deadline sheet from your actual contracts and update it each year.
A recovery workflow for aging cardiology claims
Pull the detail and sort by cause
The Maryland Department of Health’s billing manual for local health departments advises printing the detail behind over-90 balances to analyze the source and nature of each account. Do the same here. Export every claim past 90 days with payer, CPT code, denial code, date of service, and the date of the last payer response. Then group by cause: no response, rejected before processing, denied for bundling or modifiers, denied for authorization, denied for medical necessity.
The grouping matters because the fix differs by group. Twenty claims denied with CO-236 for the same payer and code pair usually share one root cause.
Rank by dollars and deadline
Work the oldest appeal clocks first, then the highest balances. Cardiac catheterization codes (93458 to 93461) and nuclear imaging carry more value per claim than a routine ECG, so a ten-minute call on one of them pays better than a morning of small balances.
Choose the right remedy
| Situation | Remedy | Clock to watch |
|---|---|---|
| Claim rejected before processing (front-end edit, bad ID) | Correct and resubmit | Original timely filing limit |
| Denial caused by a clerical error or omission | Request reopening from the MAC or payer | Set by the contractor or contract |
| Denial on substance (medical necessity, disputed bundling) | Formal appeal; redetermination for Medicare | 120 days from the notice |
| No response from payer | Check claim status, then resubmit or escalate | Original timely filing limit |
No-response claims are the easiest money in the backlog and the most neglected. A status check by phone or portal often reveals a claim the payer never received.
Build the appeal packet
Attach both documents when a same-day E/M and test are disputed: the office note showing the separate problem addressed, and the signed test report with its independent interpretation. Cite the NCCI modifier indicator when you argue a modifier is allowed. For medical necessity, quote the payer’s own coverage policy back to it and point to the documented symptoms that meet it.
For authorization denials, ask whether the payer accepts retroactive authorization. Policies vary by payer, and some allow a short window after the service.
Preventing the next 90-day backlog
Recovery is half the job. The other half is changing what feeds the bucket.
- Track denials by reason code monthly, not only by payer. If CO-4 climbs after a charge master update, the default modifier is probably wrong.
- Run NCCI edit checks before submission, and refresh them every quarter when the tables change.
- Flag every service that needs prior authorization in the scheduling system, and record the authorization number on the claim.
- Review the over-90 report weekly, grouped by cause, with a named owner for each group.
- Audit documentation for modifier 25 and modifier 26 claims before they leave the building.
Students preparing for billing certifications can practice this directly: take a sample aging report, sort it by denial code, and identify which deadline applies to each line.
Where to start with cardiology A/R over 90 days
Start by measuring cardiology A/R over 90 days by date of service, compare it against a fixed target between 12 and 20 percent, and sort the balance by denial cause. Check the notice date on every Medicare denial against the 120-day redetermination window, since that deadline, not the service date, decides what can be appealed. Then work no-response claims, clerical errors, and high-value cath and nuclear studies before anything else.



