Palpitations ICD-10 Code Complete Coding Guide for R00.2, Documentation and Billing Accuracy (2026)

A patient says her heart "flutters" after her second coffee. Another describes a pounding beat that wakes him at 3 a.m. Both complaints end up in the same place on the claim: ICD-10-CM code R00.2, Palpitations, at least until the workup finds something more specific. That last condition is where most errors with the palpitations ICD-10 code begin.
This guide explains what R00.2 includes, which Official Guidelines decide whether it belongs on a claim, how it interacts with the arrhythmia codes in categories I47 to I49, and what the FY2027 code set (effective October 1, 2026) changed around it.
What ICD-10 code R00.2 covers
R00.2 is a valid, billable code in Chapter 18 of ICD-10-CM, Symptoms, signs and abnormal clinical and laboratory findings, not elsewhere classified (R00 to R99). Its single inclusion term is "awareness of heart beat." The code entered U.S. use on October 1, 2015, replacing ICD-9-CM 785.1.
The definition describes the patient's experience, not a tracing. A 12-lead ECG can be completely normal while the complaint is genuine, and a dangerous rhythm can produce no sensation at all. Keep that distinction in mind; every coding decision below depends on it.
How R00.2 fits within category R00
Category R00 (Abnormalities of heart beat) contains five billable codes.
R00.0 Tachycardia, unspecified
Includes rapid heart beat and sinus tachycardia NOS, and carries an Excludes1 note for inappropriate sinus tachycardia (I47.11).
R00.1 Bradycardia, unspecified
Covers sinus and vagal bradycardia and excludes neonatal bradycardia (P29.12).
R00.2 Palpitations
Sits between them with its single inclusion term.
R00.8 Other abnormalities of heart beat
A residual code for documentation that fits none of the first three.
R00.9 Unspecified abnormalities of heart beat
A residual code for documentation that fits none of the first three.
At the category level, R00 carries an Excludes1 note for abnormalities originating in the perinatal period (P29.1-) and an Excludes2 note for specified arrhythmias (I47 to I49).
That Excludes2 note confuses students. Technically it permits an R00 code and an I47 to I49 code on the same claim. In practice, guideline I.B.5 usually blocks the pairing, because palpitations are routinely associated with most arrhythmias. The Excludes note answers whether two codes can coexist; the integral-symptom rule answers whether they should.
R00.2 and R00.0 are a different matter. Palpitations are a symptom the patient reports, while tachycardia is a sign the clinician measures. When the provider documents both (for example, a racing sensation plus a recorded heart rate of 118), both codes can be reported. A subjective "racing heart" with a normal measured rate supports R00.2 alone.
When to report the palpitations ICD-10 code
Three parts of the ICD-10-CM Official Guidelines for Coding and Reporting, published by CMS and NCHS, govern R00.2.
Section I.B.4
Allows codes for signs and symptoms when the provider has not established a related definitive diagnosis.
Section IV.H
Applies to outpatient and physician-office coding. Diagnoses documented as "probable," "suspected," "questionable," "rule out," "compatible with," "consistent with" or "working diagnosis" are not coded. The coder reports the condition to the highest degree of certainty for that encounter, which for an unexplained palpitation complaint is R00.2.
Section I.C.18
Permits a Chapter 18 code as the first-listed diagnosis when no related definitive diagnosis exists.
The practical result: R00.2 is correct at the first primary care visit, in the emergency department (an outpatient setting), and at a cardiology consultation that ends with a monitor order rather than a diagnosis.
When R00.2 does not belong on the claim
The most common reason is a confirmed explanation. Once the provider documents atrial fibrillation (I48.-), supraventricular tachycardia (I47.1-), premature atrial contractions (I49.1) or premature ventricular contractions (I49.3) as the cause, the arrhythmia code replaces R00.2 under guideline I.B.5.
A second exclusion is non-cardiac but just as firm. When the provider attributes the palpitations to panic disorder (F41.0), the symptom is part of that diagnosis; palpitations are one of the listed symptoms of a panic attack in the American Psychiatric Association's DSM-5. Report F41.0 alone.
Guideline I.B.6 provides the exception. Symptoms that are not routinely associated with a confirmed condition may still be coded. A patient seen for type 2 diabetes follow-up who also reports new, unexplained palpitations can receive both E11.- and R00.2, because diabetes does not account for the symptom.
Newborns are a separate case: the Excludes1 note sends perinatal heart rate abnormalities to P29.1-.
Coding scenarios
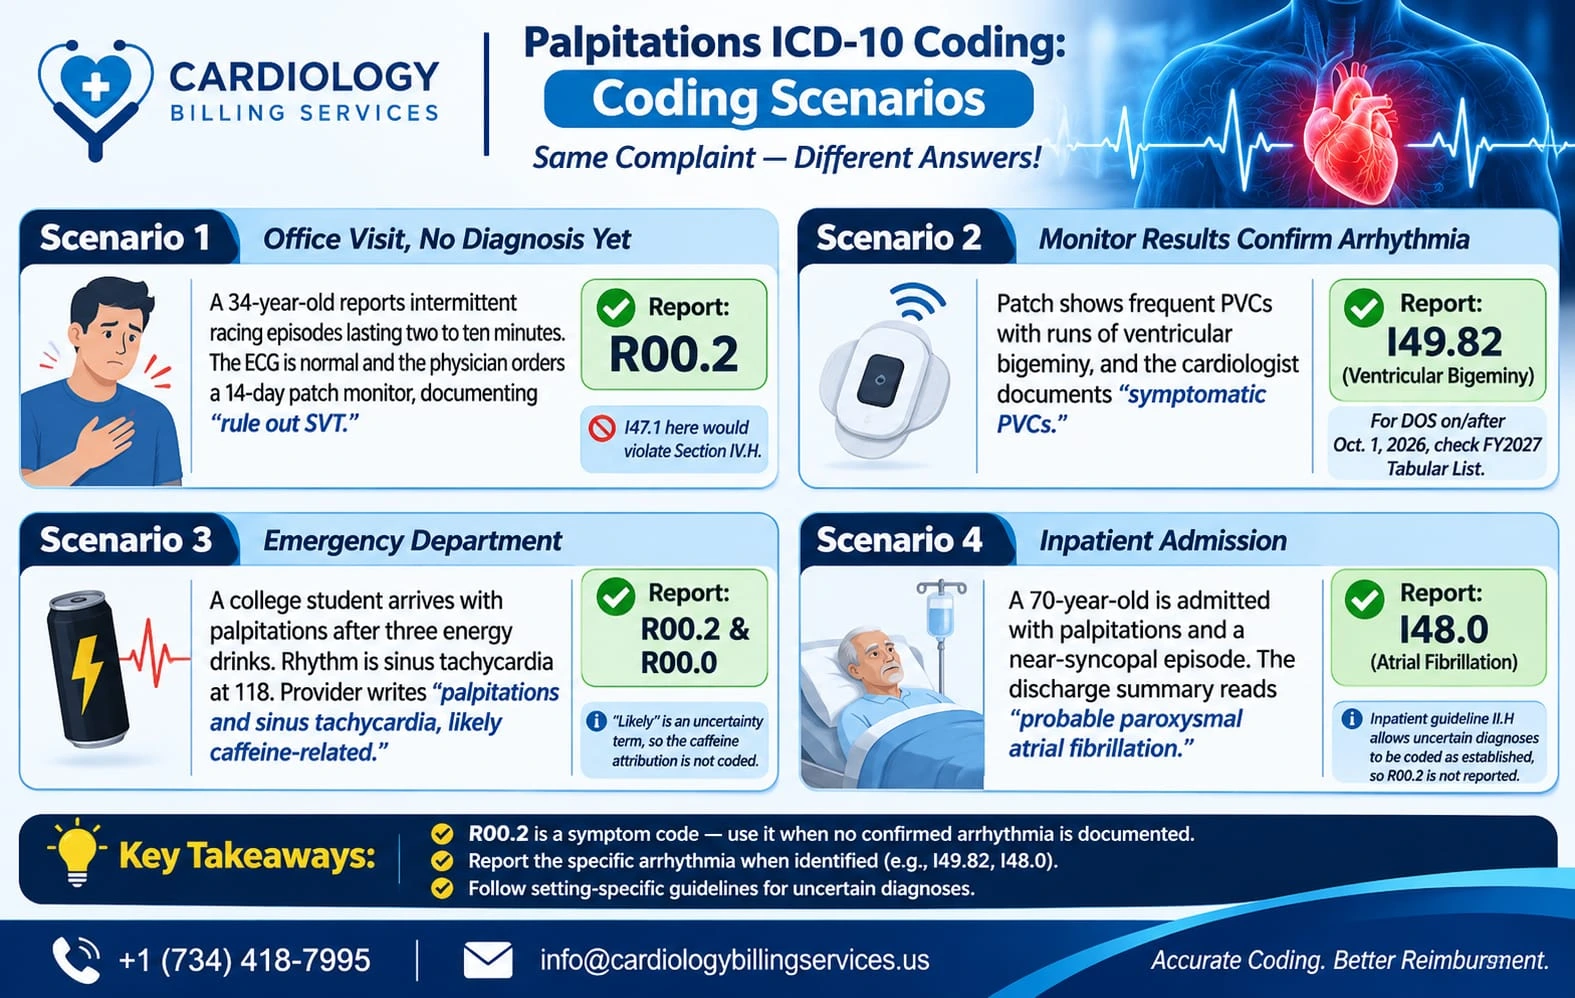
Office visit, no diagnosis yet
A 34-year-old reports intermittent racing episodes lasting two to ten minutes. The ECG is normal and the physician orders a 14-day patch monitor, documenting "rule out SVT." Report R00.2. Coding I47.1- here would violate Section IV.H.
Monitor results are back
At follow-up, the patch shows frequent PVCs with runs of ventricular bigeminy, and the cardiologist documents "symptomatic PVCs." R00.2 drops off. Report the confirmed arrhythmia, and for dates of service on or after October 1, 2026, check the FY2027 Tabular List for the new code I49.82 (ventricular bigeminy) when bigeminy is documented.
Emergency department
A college student arrives with palpitations after three energy drinks. Rhythm is sinus tachycardia at 118. The provider writes "palpitations and sinus tachycardia, likely caffeine-related." Report R00.2 and R00.0. "Likely" is an uncertainty term, so the caffeine attribution is not coded in this outpatient encounter.
Inpatient admission
A 70-year-old is admitted with palpitations and a near-syncopal episode. The discharge summary reads "probable paroxysmal atrial fibrillation." Inpatient guideline II.H allows uncertain diagnoses documented at discharge to be coded as if established, so I48.0 is reported and R00.2 is not. Same complaint, different setting, different answer.
Documentation that supports R00.2
Coders cannot add detail the provider never recorded, so documentation quality is a provider responsibility with direct billing consequences. A note that supports R00.2, and the testing that follows it, covers several areas.
Start with the episodes themselves: when they began, how long they last, how often they occur and what sets them off. The character of the sensation belongs in the note too, whether fast, slow, regular, irregular or described as "skipped" beats. Associated symptoms such as syncope, chest pain or dyspnea change the clinical picture and the testing a payer will accept.
The history should also record caffeine, alcohol and stimulant use, prescription and over-the-counter medications, and any family history of sudden cardiac death or inherited arrhythmia. Exam findings and the provider's ECG interpretation complete the record.
These details are clinically meaningful, not box-checking. In "Outpatient Approach to Palpitations," published in American Family Physician in July 2011, Randell K. Wexler, Adam Pleister and Subha Raman reported likelihood ratios for an arrhythmic cause of 2.7 for visible neck pulsations, 2.3 for palpitations that affect sleep, 2.2 for palpitations at work and 2.0 for known heart disease. The same article cites a series of 190 consecutive patients (Weber and Kapoor) in which the cause was cardiac in 43%, psychiatric in 31%, miscellaneous in 10% and unknown in 16%.
That last figure matters for coding. In roughly one patient in six, no cause was ever established, which means R00.2 can legitimately remain the final diagnosis after a complete workup.
Billing accuracy: pairing R00.2 with diagnostic services
R00.2 most often supports the medical necessity of cardiac rhythm testing. The CPT codes it is most often paired with follow a typical workup sequence.
The first test is usually a routine 12-lead ECG with interpretation and report.
Holter monitoring for up to 48 hours.
Longer external ECG recording, from more than 48 hours up to 15 days, a family added on January 1, 2021.
External event recorders worn for up to 30 days.
Mobile cardiac telemetry.
For Medicare patients, ambulatory ECG coverage falls under National Coverage Determination 20.15 (Electrocardiographic Services), and many Medicare Administrative Contractors publish billing articles listing covered diagnosis codes. Confirm that R00.2 appears on your contractor's list before relying on it, and point each claim line to the diagnosis that justifies it.
The ordering visit carries R00.2 because no diagnosis exists yet. The physician who interprets the monitor codes from the recording; if it shows atrial flutter, the interpretation claim reports I48.- even though the order carried R00.2. Both claims are correct.
For risk adjustment, R00.2 does not map to a payment HCC in the CMS-HCC V28 model. A confirmed arrhythmia often does, so leaving a patient coded at the symptom level after a diagnosis has been documented understates risk as well as accuracy.
What changed for FY2026 and FY2027
R00.2 itself was unchanged in the FY2026 code set (effective October 1, 2025) and again in FY2027 (effective October 1, 2026). The neighboring arrhythmia codes did change. FY2027 added 238 entries, 190 of them billable, according to CMS release files.
I47.22
Catecholaminergic polymorphic ventricular tachycardia
I49.81
Brugada syndrome
I49.82
Ventricular bigeminy
I49.89
Other specified cardiac arrhythmias
With those additions, I49.8 became a non-billable heading. Claims submitted with I49.8 for dates of service on or after October 1, 2026 will be rejected. Earlier, the FY2023 update split supraventricular tachycardia into I47.10, I47.11 and I47.19, which is why R00.0 now excludes inappropriate sinus tachycardia (I47.11).
Frequent R00.2 errors
The error that appears most often is reporting R00.2 alongside the arrhythmia that explains it. Close behind is coding a "rule out" or "suspected" arrhythmia in an outpatient setting, which Section IV.H prohibits. Problem lists cause a quieter version of the first mistake: R00.2 gets carried forward visit after visit even though a diagnosis was documented months earlier.
Two smaller errors round out the list. R00.0 is sometimes assigned for a subjective racing sensation when no tachycardia was measured.
I49.8 is still being submitted for dates of service after September 30, 2026, when it stopped being billable.
Key points for coders and providers
R00.2 is a billable symptom code for awareness of the heartbeat, reported when no definitive cause has been established. In outpatient settings it replaces any "probable" or "rule out" arrhythmia; in inpatient settings, guideline II.H can override it at discharge. Once a cause is confirmed, the specific I47 to I49, I48 or F41.0 code takes its place, and the FY2027 additions (I47.22, I49.81, I49.82, I49.89) give that specific code more precision than before. Because about 16% of patients in the Weber and Kapoor series never received an explanation, R00.2 can also be the accurate final answer, provided the record shows the workup that was done.